News
The Surgeon Told the Rookie Nurse to Stand Back — Then a Navy SEAL Saw Her Dog Tags and Saluted
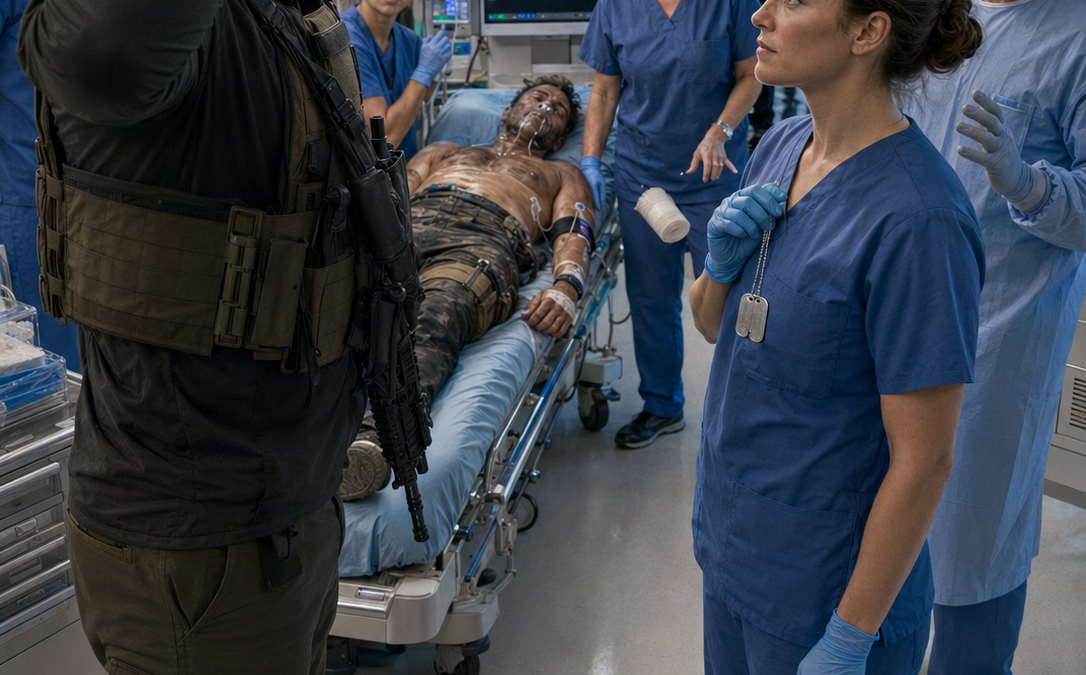

PART 2
Evelyn Mercer had not been hiding a secret identity.
That distinction mattered to her.
Human Resources knew exactly who she was.
Her résumé listed eighteen years of critical-care nursing.
Seven years in emergency and trauma units.
Eleven years in air-medical transport.
Nine years in leadership, overlapping with clinical work.
Doctor of Nursing Practice.
Certified flight registered nurse.
Former clinical director.
Publications.
Committee work.
Disaster-response planning.
Nothing classified.
Nothing concealed.
Dr. Halvorsen had never read beyond the two-page onboarding summary.
Carla had assumed Evelyn was rusty because she asked questions.
Other nurses assumed she was quiet because she lacked confidence.
Evelyn let them.
Because after twenty years of being the person everyone called when something went wrong, anonymity felt medicinal.
The next afternoon Halvorsen requested meeting.
Evelyn declined.
He requested again.
She accepted because chief trauma surgeon can make “request” annoyingly persistent.
His office overlooked mountains.
He did not offer coffee.
“You let me talk to you like you were inexperienced.”
Evelyn sat.
“You assumed I was inexperienced.”
“That’s different?”
“Yes.”
“How?”
“You never asked.”
Halvorsen leaned back.
“That seems convenient.”
“It is factual.”
He looked irritated.
“You could have corrected me.”
“I corrected you when patient safety required it.”
“And every other time?”
“It didn’t.”
That answer annoyed him more.
“Why come here?”
“I needed job.”
“You could lead another program.”
“I didn’t want to.”
“Why?”
Evelyn stared at his desk.
There were two framed journal covers bearing his name.
A family photo faced away from her.
She said:
“My father had a stroke three years ago.”
Halvorsen’s expression changed slightly.
“I’m sorry.”
“He lived.”
“Okay.”
“I left Front Range to care for him.”
That was only half.
She continued:
“He needed eighteen months of rehabilitation.”
“I thought I would return to transport leadership afterward.”
“But?”
“He died eight months ago.”
Silence.
Not from stroke.
Pancreatic cancer discovered later.
Fast.
Unfair.
Evelyn had spent years teaching strangers how to navigate catastrophic illness, then discovered none of it made being daughter easier.
After funeral, Front Range offered old executive role back.
She visited operations center.
Saw office.
Saw wall of incident maps.
Saw twenty-seven unread leadership emails.
Turned around.
“I didn’t want to be responsible for everyone again.”
Halvorsen listened.
Evelyn continued:
“I wanted twelve-hour shift.”
“One unit.”
“Patients in front of me.”
“Go home when shift ends.”
“That’s all.”
He said:
“You’re overqualified.”
She looked directly at him.
“That phrase is often another way of telling someone their current choice is invalid.”
Halvorsen went silent.
Good.
Then:
“About last night.”
“Yes.”
“I was wrong about airway.”
“You changed decision.”
“After arguing.”
“Yes.”
“I shouldn’t have spoken to you that way.”
“No.”
That surprised him.
He had expected gracious absolution.
Evelyn added:
“You also shouldn’t speak to inexperienced nurses that way.”
There it was.
Not because she had hidden prestige.
Not because she turned out important.
Because contempt damages communication.
Halvorsen looked away.
“You think I’m abusive.”
“I think you use competence as permission to humiliate people.”
His jaw tightened.
“You’ve known me three weeks.”
“I’ve watched you twenty-two shifts.”
Silence.
She continued:
“You’re an excellent surgeon.”
He looked back.
“You make fast decisions.”
“You change course when evidence becomes undeniable.”
“That’s valuable.”
Halvorsen seemed suspicious of compliment.
Then:
“But people wait too long to give you evidence because they’re afraid how you’ll respond.”
That one hurt.
He said nothing.
Evelyn stood.
“I have shift.”
At door he asked:
“Why didn’t you take over last night?”
She turned.
“Take over what?”
“Disaster coordination.”
“Because you had incident command.”
“I mean clinically.”
“I wasn’t credentialed for leadership here.”
“You had more disaster experience than anyone in room.”
“Experience doesn’t erase chain of command.”
He stared.
Evelyn continued:
“My job was to notice, escalate, and help.”
“Not perform résumé.”
She left.
That sentence stayed.
The hospital initiated routine after-action review of plant explosion.
No investigation into Halvorsen specifically.
Mass casualties always get reviewed.
What worked.
What did not.
Patient flow.
Decontamination.
Blood use.
Imaging bottlenecks.
Communication.
The first major finding was uncomfortable:
Contaminated patient almost entered clean treatment area.
Not because EMS failed entirely.
Field decon had occurred.
But chemical identification changed during transport.
Handoff note did not reach receiving team before arrival.
Evelyn had noticed physical clue.
System should not depend on that.
Second:
Airway escalation worked once concern identified.
Third:
Nursing concerns were not consistently verbalized during first hour.
Carla interviewed staff.
Several admitted they hesitated to challenge physicians.
Not only Halvorsen.
But mostly Halvorsen.
One nurse said:
“If you’re wrong, he makes you regret speaking.”
That appeared anonymously in report.
Halvorsen read it alone.
Evelyn did not know.
Two days later he entered Bay Four where a twenty-three-year-old nurse named Lily Grant was caring for motorcycle patient.
Lily said:
“Dr. Halvorsen, something doesn’t look right.”
He almost replied:
“What?”
Sharp.
Automatic.
Stopped.
“What are you seeing?”
Lily blinked.
Then explained.
Patient’s abdominal pain increasing.
Heart rate trending upward.
Blood pressure still acceptable.
Halvorsen reassessed.
Ordered repeat imaging and labs.
Nothing catastrophic emerged.
No hidden bleed.
Pain from expanding soft-tissue injury.
Treatment adjusted.
Afterward Lily said:
“Sorry. Guess it was nothing.”
Halvorsen heard Evelyn’s voice somewhere irritating inside skull.
He said:
“No.”
Lily looked.
“You noticed change.”
“We checked.”
“That’s appropriate.”
She stared as if he had grown another head.
Halvorsen walked away.
Change rarely feels cinematic.
Usually it feels awkward.
PART 3
Evelyn became famous inside Granite Ridge against her will.
Not publicly.
Worse.
Among coworkers.
People started asking questions.
“Did you really land in mountain storms?”
“Did you run helicopter program?”
“Were you at the canyon bus crash?”
“Did you invent the Mercer triage model?”
“No.”
“Yes.”
“Not exactly.”
“Committee.”
Her favorite answer became:
“Please chart your patient.”
Carla enjoyed this immensely.
Then administration made predictable mistake.
Chief Nursing Officer requested meeting.
Offered Evelyn role:
Director of Emergency Preparedness and Critical Care Integration.
Evelyn declined within four minutes.
“May I ask why?”
“No.”
The executive blinked.
Evelyn softened.
“I just started bedside again.”
“We could create hybrid role.”
“No.”
“You have rare experience.”
“So do many people.”
“We need leadership.”
“You have leaders.”
“We need you.”
That sentence was dangerous.
Evelyn said:
“No organization should need one specific person that badly.”
The executive thought.
“Then what would you recommend?”
Better question.
Evelyn answered.
“Train more people.”
That became compromise.
She agreed to one six-week project reviewing disaster readiness while remaining bedside nurse.
No title change.
No office.
No salary negotiation initially, until Carla threatened bodily harm.
“Your expertise is labor.”
Evelyn sighed.
“Fine.”
She negotiated differential.
Good.
The review uncovered nothing scandalous.
That was important.
Granite Ridge was good hospital.
But good systems contain fragile assumptions.
Emergency chemical-decon cache was stored too far from ambulance entry.
Disaster call tree relied on one outdated phone list.
Critical care transfer protocols assumed air transport would be available.
During winter storms, often not.
Most concerning:
The hospital’s disaster plan treated physicians as decision-makers and nursing/respiratory/logistics as implementers.
Real emergencies did not respect that hierarchy.
Evelyn proposed cross-functional command drills.
Halvorsen opposed first version.
“Too many voices.”
Evelyn said:
“Too many voices without structure, yes.”
“Then why add people?”
“Because information lives where work happens.”
He folded arms.
“Give example.”
“The plant patient.”
Halvorsen groaned.
“You’re going to use that forever?”
“Probably.”
She continued:
“EMS knew exposure.”
“Respiratory saw voice change.”
“Nursing saw contamination.”
“Physician owned medical decision.”
“Environmental services understood clean-zone risk.”
“Security controlled entrance.”
“No single role had complete picture.”
Halvorsen frowned.
“So?”
“So command system should gather information without turning every observation into vote.”
He liked that.
“Not democratic medicine.”
“No.”
“Defined authority?”
“Yes.”
“Open input?”
“Yes.”
He nodded slowly.
That became framework.
Six months later Granite Ridge tested it in full-scale drill.
Scenario:
Winter freeway pileup.
Power interruption.
Fifty simulated casualties.
Communications degraded.
Evelyn did not command.
A forty-two-year-old emergency physician named Priya Nair did.
Halvorsen ran surgical branch.
Carla nursing operations.
Facilities chief handled infrastructure.
Evelyn observed.
Drill failed beautifully.
Phones overloaded.
One simulated patient got “lost” between imaging and holding.
Supplies went to wrong bay.
Two leaders issued conflicting messages.
Evelyn smiled.
Halvorsen saw.
“You’re enjoying this.”
“Yes.”
“It’s a disaster.”
“Fake disaster.”
“Difference?”
“This one teaches without funerals.”
Good.
After-action review was brutal.
They fixed.
Three months later reality arrived.
Spring wildfire west of city.
Not huge initially.
Wind changed.
Smoke corridor shifted.
A long-term care facility evacuated eighty-two residents.
Granite Ridge received nineteen medically complex patients over ninety minutes.
Not classic trauma.
Oxygen-dependent patients.
Dementia.
Mobility issues.
Medication lists incomplete.
One man without hearing aids.
One woman clutching cat carrier with no cat because daughter had taken cat separately.
Chaos of ordinary vulnerability.
Halvorsen was not needed surgically.
He still came.
Evelyn assigned medical-surgical intake.
A junior unit clerk said:
“We’re missing three medication packets.”
Old culture might have ignored.
Evelyn asked:
“Which patients?”
They identified.
Pharmacy contacted facility.
Problem solved before medication delays.
A respiratory therapist said oxygen manifold pressure was dropping faster than expected.
Facilities responded.
Temporary supply increased.
No crisis.
A certified nursing assistant mentioned one evacuated resident normally became severely agitated if separated from red blanket.
Someone found blanket in transport bag.
No sedation needed.
Small details.
Real resilience.
Later Halvorsen stood beside Evelyn.
“This is what you meant.”
“What?”
“Information lives where work happens.”
“Yes.”
He looked around.
No dramatic hero.
Just dozens of people noticing things.
He said:
“I used to think command meant reducing noise.”
“It does.”
“But?”
“You have to distinguish noise from weak signals.”
Halvorsen nodded.
“Annoying.”
“I’ve heard.”
Disclaimer: This story is fictional and created for entertainment purposes only.
Any names, characters, places, or events are fictitious or used fictitiously.
No real person or organization is intended to be portrayed.





