“Daddy Keeps Hiding His Left Arm,” the Little Girl Whispered — The Charge Nurse Looked Again and Her Face Changed
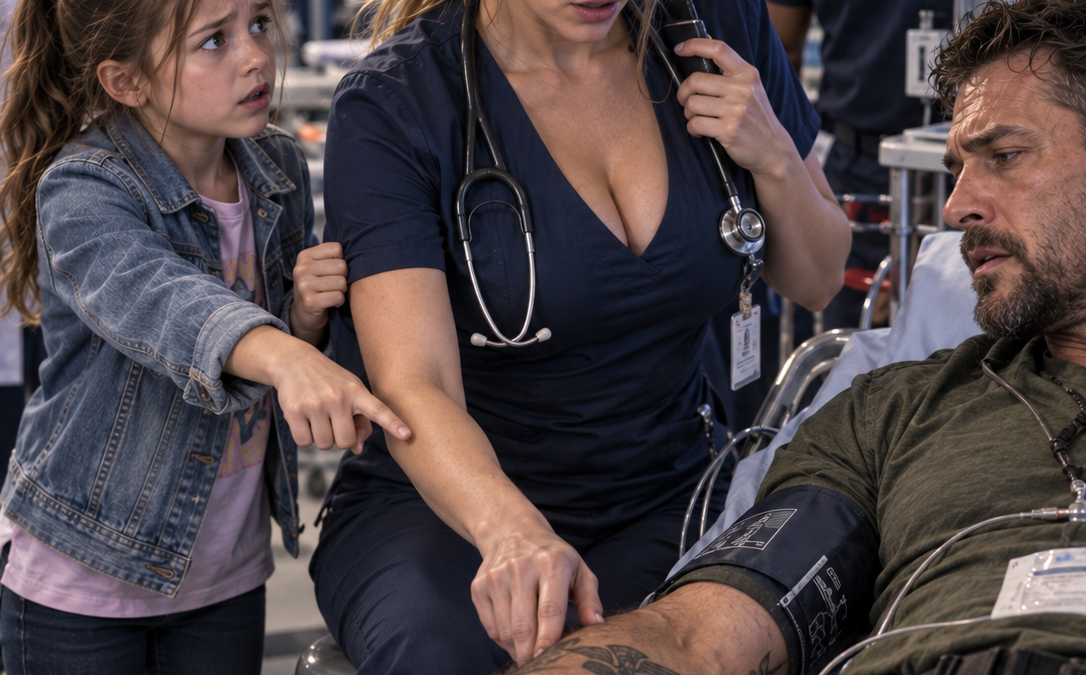

PART 2
The cardiothoracic surgeon arrived eight minutes later.
Dr. Priya Raman was forty-nine, compact, direct, and completely uninterested in Ethan’s military rank.
She placed the CT image on the monitor.
“The tear begins here.”
She pointed at the ascending aorta.
“It travels through the arch and compromises blood flow into your left subclavian artery. That explains the pulse difference.”
Ethan asked the question Sophie was too frightened to ask.
“If we had gone upstairs for observation?”
Dr. Raman did not dramatize.
“This can worsen unpredictably. We found it before rupture, tamponade, stroke, or complete loss of blood flow to the arm.”
Sophie’s lower lip trembled.
Ethan noticed.
“Hey.”
She looked at him.
“Eyes on me.”
It sounded like a command.
Then he softened it.
“Please.”
She stepped closer.
“I’m going to surgery. The doctors are going to fix the bad part.”
“Are you going to die?”
Nobody in the room moved.
Ethan opened his mouth.
The instinctive answer was obvious.
No.
Of course not.
He had given Sophie certainty for years whether he possessed it or not.
This time he stopped.
“I don’t know.”
Her eyes filled.
“But I’m going to do exactly what they tell me.”
Sophie nodded once.
“And you?”
“What?”
“You’re going to let Mara stay with you until Aunt Rachel gets here.”
Sophie looked at Mara.
Mara said:
“I can do that.”
Ethan reached for his daughter.
She leaned carefully against him.
For several seconds, rank and monitors and surgical urgency disappeared.
Then transport arrived.
Sophie whispered into his shoulder:
“You have to come home.”
Ethan closed his eyes.
“I’m going to work very hard on that.”
As the team prepared to move him, Dr. Raman was still studying the CT.
Then she frowned.
She enlarged an older comparison window.
“Captain Mercer, have you ever been told you have an ascending aortic aneurysm?”
Ethan looked confused.
“No.”
“Ever had a chest CT before?”
“Plenty.”
“Why?”
“Blast exposure. Diving evaluations. Shoulder injury. Military medicine likes pictures.”
Dr. Raman tapped the screen.
“There’s a prior study in your record from eighteen months ago.”
Ethan stared.
“What does it say?”
She did not answer immediately.
Mara stepped closer.
The report had been performed at a Navy medical facility after Ethan developed persistent upper-back pain following a training accident.
The lungs had been normal.
No fracture.
No pulmonary injury.
But under incidental findings:
Ascending thoracic aorta measures approximately 5.1 cm. Recommend cardiothoracic evaluation and surveillance.
Ethan read the line.
Then again.
“No.”
Dr. Raman said quietly:
“This was already enlarged eighteen months ago.”
“Nobody told me.”
The chart status showed:
CRITICAL INCIDENTAL FINDING — FOLLOW-UP REQUIRED.
Below it:
PATIENT NOTIFIED.
Ethan looked at Mara.
“I was never notified.”
“Maybe someone called—”
“I would remember someone telling me the largest artery in my body was five centimeters wide.”
Dr. Raman closed the record.
“We deal with this later. Right now I need to repair your aorta.”
Correct priority.
Ethan was taken toward surgery.
Sophie watched until the doors closed.
Her aunt Rachel arrived fourteen minutes later and found her sitting beside Mara.
Rachel Mercer was Ethan’s younger sister, a high-school principal who entered the waiting room at a run and stopped only when Sophie stood.
“Is he—”
“He’s in surgery.”
Rachel hugged her niece.
Mara began explaining.
Then Sophie said:
“They already knew.”
Rachel looked at her.
“What?”
“The computer said they already knew Daddy’s heart pipe was too big.”
Mara corrected gently:
“His aorta.”
Sophie nodded.
“But nobody told him.”
Rachel looked toward Mara.
Mara said:
“There is an old imaging report with a recommended follow-up.”
“And it says he was notified?”
“Yes.”
“But he says he wasn’t?”
“Yes.”
Rachel sat slowly.
“How does that happen?”
Mara had worked in hospitals long enough to know the answer was usually not one dramatic mistake.
It was handoffs.
Routing.
Software.
Assumptions.
People believing another person had completed a task.
But she did not know what happened here.
“I don’t know.”
At 2:11 a.m., while Ethan remained on bypass in Operating Room Four, a hospital quality nurse helped Mara open the audit trail for the old report.
The critical finding had been routed correctly.
First to radiology.
Then to Ethan’s primary military clinic.
Then to a unit medical coordinator.
A notification task was generated.
The status changed to PATIENT NOTIFIED twenty-seven hours later.
Rachel leaned toward the screen.
“Who closed it?”
The quality nurse pulled up the identifier.
Then stopped.
“That’s strange.”
“What?”
“The account belongs to Naval Special Warfare Medical Detachment Seven.”
Rachel frowned.
“Ethan left Detachment Seven years ago.”
The nurse checked the timestamp.
Then the facility code.
Then another field.
Her face changed.
“This wasn’t closed by a person.”
Mara looked at her.
“What do you mean?”
“The status was changed during a bulk record migration.”
The new electronic system had automatically converted thousands of legacy follow-up tasks into completed notification statuses when their originating clinic queues were retired.
No phone call.
No letter.
No conversation.
Just a migration rule.
And Ethan Mercer’s potentially lethal aneurysm warning had been converted from FOLLOW-UP REQUIRED to PATIENT NOTIFIED by software.
PART 3
Ethan’s operation lasted six hours and forty-three minutes.
Dr. Raman replaced the damaged segment of his ascending aorta with a synthetic graft and repaired the arch enough to restore reliable blood flow into the vessels feeding his brain and left arm.
At 5:58 a.m., she entered the waiting room.
Sophie was asleep with her head in Rachel’s lap.
Mara had finished her shift two hours earlier.
She was still there.
Dr. Raman looked at them.
“He made it through surgery.”
Rachel closed both hands over her face.
Mara exhaled.
Sophie woke instantly.
“Is Daddy alive?”
“Yes.”
That was the first answer nobody needed to qualify.
“He’s alive.”
Sophie began crying before Dr. Raman finished explaining.
Not loudly.
The exhausted crying of a child who had spent eight hours trying to behave like an adult.
Mara sat beside her.
“You did your part.”
“I only told you his hand looked weird.”
“Yes.”
Sophie wiped her nose.
“That’s not much.”
Mara looked toward the surgical doors.
“Sometimes the important thing is noticing one fact everyone else thinks is small.”
Ethan spent two days sedated.
When he woke, his first question was not about surgery.
“Sophie?”
Rachel stood beside him.
“She’s at school.”
His face tightened.
“School?”
“You wanted normal.”
“Not that normal.”
“She wanted to go.”
Then Sophie appeared around the doorway.
Rachel had lied.
Ethan’s eyes filled.
Sophie walked toward him slowly.
The ICU frightened her.
Tubes.
Lines.
Monitors.
Machines breathing numbers into the room.
Ethan lifted his right hand.
She took it.
Then immediately looked at his left.
He smiled weakly.
“Checking?”
“Yes.”
“Color okay?”
She compared both hands.
“Better.”
That became their first joke after surgery.
The investigation into the old report was less funny.
The hospital where Ethan now lay was not the facility that had missed the follow-up.
But because the records shared a federal health-information network, military medical quality officers were notified.
Within three weeks, a joint review began.
The migration had happened eighteen months earlier when several legacy medical-clinic queues were consolidated.
One rule had been designed to prevent thousands of obsolete tasks from remaining permanently open.
For routine administrative items, that made sense.
For critical imaging follow-up, it was disastrous.
The migration had no reliable distinction between:
patient actually contacted,
notification attempted,
clinic responsibility transferred,
and task administratively closed.
All could become the same final status.
PATIENT NOTIFIED.
Ethan’s aneurysm was not the only record affected.
Investigators reviewed thousands.
Most involved ordinary follow-up.
Then they found twenty-seven critical or potentially significant imaging findings whose closure status could not be verified.
Twenty-one patients had eventually received appropriate care elsewhere.
Six required immediate contact.
Three needed new imaging.
One older retired sailor had a lung nodule that required biopsy.
Another patient had an enlarging kidney lesion.
None of those findings automatically meant cancer or catastrophe.
But none should have disappeared inside a database either.
Ethan learned this during cardiac rehabilitation.
His first reaction was anger.
“Who signed off on the migration?”
Rachel sat beside him.
“Don’t.”
“Don’t what?”
“Turn this into a target.”
“Somebody approved it.”
“Yes.”
“That matters.”
“It does. But you know what you’re doing.”
He did.
He was building a person he could blame.
It was easier than accepting that nobody had intentionally decided his life did not matter.
The review found the migration had been tested.
Information technology staff verified that task counts transferred correctly.
Clinical staff verified sample patient records.
But nobody specifically tested whether critical follow-up semantics changed when old queues were closed.
The migration team believed clinic owners would validate their own high-risk items.
Clinic owners believed the migration preserved high-risk flags automatically.
Both assumptions were documented.
Both were wrong.
Captain Ethan Mercer, who had spent a career teaching men that assumptions killed, sat silent when he read that.
Sophie was doing homework across the room.
She looked up.
“What?”
“Nothing.”
She narrowed her eyes.
He corrected himself.
“Actually, something.”
Progress.
“The computer mistake happened because people thought somebody else was checking.”
Sophie considered that.
“Like when you thought the doctors knew “Daddy Keeps Hiding His Left Arm,” the Little Girl Whispered — The Charge Nurse Looked Again and Her Face Changedabout your arm?”
Ethan stared at her.
Rachel laughed.
He did not.
Because she was right.
He had assumed the medical team knew everything important because he had answered the questions they asked.
They had assumed he would mention anything important.
Sophie had no such assumptions.
She knew her father.
His hand looked wrong.
So she said it.





