A Navy SEAL Demanded My Supervisor While His Heart Was Failing — Then He Grabbed My Sleeve and Exposed the Secret I’d Buried

PART 2
Aaron Pike survived surgery.
The impact from the rollover had caused a small cardiac injury that slowly bled into the sac surrounding his heart.
Not enough to announce itself immediately.
Enough to become lethal over time.
Dr. Shah relieved the pressure and repaired the injury.
By sunrise, Pike was sedated in intensive care.
I should have been relieved.
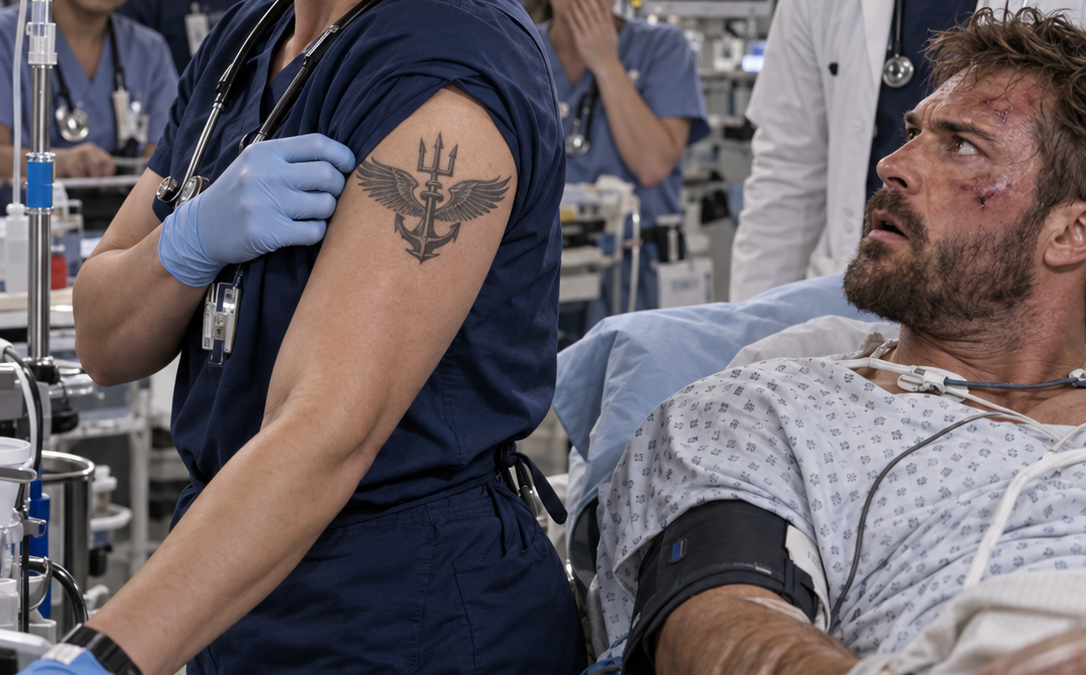
Instead, I sat alone in the locker room staring at the tattoo on my arm.
JMSU-4.
The ink was nine years old.
The life attached to it felt older.
Joint Medical Support Unit Four did not appear in recruitment commercials.
We were not SEALs.
Not shooters.
Not people who kicked doors.
We were physicians, nurses, corpsmen, respiratory specialists and medics assigned to support units that went places ordinary hospitals never followed.
I had been Navy Nurse Corps.
Critical care.
Flight qualified.
Then selected for a joint special-operations surgical support element.
Seven years.
Three deployments.
Too many aircraft.
Too many casualties.
Too much confidence.
Then one night in 2019 had ended all of it.
I changed into jeans.
Pulled on a sweater.
Covered the tattoo.
When I opened the locker-room door, Olivia was waiting.
“You’re creepy.”
She blinked.
“What?”
“Standing outside locker rooms.”
“I wasn’t sure whether knocking would make it worse.”
“It would.”
She followed me toward the exit.
“So.”
“No.”
“I didn’t ask anything.”
“You’re about to.”
“Fine. One question.”
“No.”
“Were you really a lieutenant commander?”
I stopped.
Olivia nearly walked into me.
“Yes.”
Her eyes widened.
“You outranked my husband.”
“Congratulations.”
“He’s going to hate this.”
“Please don’t tell him.”
Her humor disappeared.
“Okay.”
That made me look at her.
She shrugged.
“You said please.”
I continued walking.
Olivia stayed beside me.
“Mercer is looking into your file.”
I stopped again.
“What?”
“He asked administration for your complete credentialing record.”
Of course he had.
“Why?”
“He says risk management needs to know whether your military experience affected your clinical decision-making.”
“That doesn’t make sense.”
“I know.”
My stomach tightened.
“What else?”
“He looked angry.”
That did make sense.
Not because I had hidden my service.
It was in my personnel file.
Navy Nurse Corps, 2009–2020.
Critical care.
Emergency nursing.
The classified assignments had been summarized.
What I had not included on my résumé were command roles, unit names, operational citations or the reason I left active service.
None of those were required for a civilian nursing position.
But people dislike discovering that someone they thought they understood has an entire history they never bothered to ask about.
At 8:16 that morning, risk management emailed me.
Meeting required before next shift.
I went home.
Slept three hours.
Woke from the same dream I had been having for six years.
Rotor noise.
Red cabin lights.
Someone shouting my name.
A monitor alarm.
Then silence.
I sat upright in bed.
My heart was pounding.
For three seconds I didn’t know what country I was in.
Then I saw my bedroom window.
Virginia sunlight.
Laundry chair.
A coffee mug I had forgotten to take downstairs.
Civilian life.
I hated how long it sometimes took to recognize it.
At three that afternoon, I returned to Chesapeake Memorial.
Risk manager Denise Warner sat across from me.
Dr. Mercer was beside her.
Chief Nursing Officer Beth Lang stood near the window.
Denise opened a folder.
“Claire, this is not disciplinary at this stage.”
“At this stage.”
She ignored that.
“Dr. Mercer raised a concern about last night’s event.”
Mercer spoke.
“You pushed for repeat imaging based on a diagnosis outside your scope.”
“No.”
His jaw tightened.
“You specifically raised tamponade.”
“After you asked what I thought the pattern suggested.”
“You directed the room.”
“I requested reassessment. You ordered the ultrasound.”
“And if I had refused?”
“I would have escalated to the trauma attending or charge physician.”
Mercer leaned back.
“There. That’s what I’m talking about.”
Beth Lang frowned.
“What?”
“She operates as if the chain of command is optional.”
I stared at him.
“Hospital escalation policy exists specifically because the chain of command can fail.”
Denise raised one hand.
“Let’s stay factual.”
Good.
Facts were easier.
We reconstructed the timeline.
Initial vitals.
Medication.
Repeat readings.
Symptoms.
My request.
Mercer’s ultrasound.
Surgical escalation.
Nothing I had done fell outside nursing scope.
That should have ended it.
Then Mercer placed another document on the table.
My military-service summary.
“Why was this not disclosed to me?”
I looked at him.
“Because you never asked me whether I used to be a Navy officer.”
“You accepted employment in my emergency department.”
“Your emergency department?”
His face reddened.
Beth intervened.
“Claire.”
I looked at her.
She continued.
“Malcolm means your prior experience may be clinically relevant.”
“It is in my credentialing file.”
“Not the special-operations assignment.”
“Because the specific unit assignment wasn’t relevant to licensure.”
Mercer said, “You spent seven years in an advanced operational medical unit.”
“Yes.”
“In what capacity?”
“Critical-care nurse.”
“That’s incomplete.”
“Yes.”
“Why?”
I felt the old door closing inside me.
Because once people heard the whole story, they stopped seeing a nurse.
They saw the woman from the investigation.
The officer who signed the launch decision.
The survivor.
The one person who came home when three others didn’t.
“I don’t discuss it.”
Mercer gave a disbelieving laugh.
“That isn’t good enough.”
“It has been for eleven months.”
“It wasn’t relevant until you started acting like this was a field hospital.”
There it was.
I stared at him.
“How exactly did I act like it was a field hospital?”
“You challenged the attending physician in front of staff.”
“Because our patient was deteriorating.”
“You turned a clinical concern into a command confrontation.”
“No. You did.”
Silence.
Beth looked down.
Denise wrote something.
Mercer’s voice became colder.
“You have a problem with authority.”
I almost laughed.
That accusation had followed me once before.
Six years ago.
Different man.
Different room.
Same tone.
I stood.
“Are we finished?”
Denise looked surprised.
“Claire—”
“If this is about scope, review the chart.”
“It is.”
“If it’s about credentialing, my records are complete.”
“They are.”
“If Dr. Mercer wants my biography because he discovered I once held a higher military rank than his patient expected, that isn’t a risk-management issue.”
Mercer stood too.
“You think this is about rank?”
“No.”
I looked directly at him.
“I think this is about being wrong in front of people.”
His face changed.
I regretted the sentence immediately.
Not because it was false.
Because it was crueler than necessary.
That was one of my problems.
When cornered, I could still use precision as a weapon.
Beth said my name quietly.
I took a breath.
“That was unnecessary.”
Mercer said nothing.
I continued.
“But the clinical record remains what it is.”
Denise closed the folder.
“No disciplinary action pending completion of chart review.”
“Fine.”
I left.
In the hallway, Olivia waited again.
“You have got to stop doing that.”
“What?”
“Materializing after meetings.”
“How bad?”
“Bad enough.”
Before I could answer, someone called from behind us.
“Nurse Donovan.”
I turned.
Aaron Pike stood twenty feet away.
Hospital gown.
Telemetry box.
One hand holding an IV pole.
A corpsman beside him looking exhausted.
Pike looked pale.
But alive.
He pointed at me.
“You.”
I sighed.
“You’re supposed to be in ICU step-down.”
“I got transferred.”
“You’re supposed to be resting.”
“I was.”
“Past tense concerns me.”
He walked closer.
Then stopped.
The arrogance from the night before was gone.
“I owe you an apology.”
“You nearly died yesterday. I’m giving you forty-eight hours before requiring manners.”
“I was an ass.”
“Accurate diagnosis.”
Olivia looked delighted.
Pike ignored her.
“I meant what I said. I owe you.”
“You don’t.”
“I also made a phone call.”
My stomach dropped.
“To whom?”
He hesitated.
That was all I needed.
“Aaron.”
It was the first time I used his first name.
“What did you do?”
“I asked somebody about JMSU-4.”
Every muscle in my back tightened.
“I told you not to.”
“You didn’t.”
“I didn’t think I had to.”
“I knew someone who served adjacent to your unit.”
“Who?”
“Retired Master Chief Dean Holloway.”
My mouth went dry.
Pike saw it.
“You know him.”
“Yes.”
“He knew you too.”
I turned away.
“Claire.”
“No.”
“He told me why you left.”
I stopped.
Olivia looked between us.
Pike’s voice softened.
“He told me you weren’t the one who failed that mission.”
And suddenly I was back inside a burning aircraft, six years younger, with three people screaming over the radio and one decision left to make.
PART 3
The mission had not failed because of enemy fire.
That would have been easier.
We understood enemy fire.
The failure was weather.
Fuel.
Timing.
And one aircraft that should never have launched.
October 2019.
Northern Iraq.
A special-operations team had taken casualties during a partnered mission.
We were the forward surgical element designated to receive them.
I was lieutenant commander and senior critical-care nurse on the flight package.
The weather was deteriorating.
Our pilot wanted another ten minutes.
Ground command wanted immediate launch.
The casualties were unstable.
A surgeon named Commander Ben Wallace looked at me.
“We wait, one of them may not make it.”
So I supported launch.
Nobody forced me.
Nobody tricked me.
I said yes.
Seven minutes later, the aircraft encountered conditions worse than forecast.
We made it back.
The second aircraft did not.
Three medical personnel died.
Two aircrew survived.
The investigation found no single person responsible.
Weather data had been incomplete.
Command pressure had influenced the decision.
The aircraft commander retained final launch authority.
Our medical urgency had been real.
Everyone had made defensible choices.
Three people were still dead.
That was the problem with official findings.
They can establish responsibility.
They cannot tell grief where to go.
Master Chief Dean Holloway had been waiting on the ground that night.
He had spent years telling me the same thing.
You did not crash that aircraft.
I spent years not believing him.
Pike found me twenty minutes after our hallway conversation.
I was standing on the staff balcony despite the cold.
He stayed near the door.
“I shouldn’t have called Holloway.”
“No.”
“I was curious.”
“That makes it better.”
“No.”
At least he didn’t try to defend himself.
“I thought you were hiding something shameful.”
I looked at him.
“Why?”
“Because I do.”
That shut me up.
He came outside.
A hospital blanket was wrapped over his shoulders.
“You’re a terrible patient.”
“I’ve been told.”
“What are you hiding?”
He stared over the parking lot.
“The rollover wasn’t random.”
I waited.
“Our training schedule had been extended twice.”
“What does that mean?”
“Fourteen-hour day became eighteen. Then we got another movement task.”
“Fatigue.”
“Yes.”
“Who approved it?”
“Our troop commander.”
“Was that improper?”
“Not automatically.”
I appreciated the distinction.
“We were behind on certification events. Everybody was tired. Nobody wanted to be the guy who said stop.”
“Did you?”
“No.”
His mouth twisted.
“I’m the senior enlisted man in that vehicle.”
There it was.
His version of my aircraft.
“Who was driving?”
“Second Class Ben Foster. Twenty-four years old.”
“Injured?”
“Bruised. Nothing serious.”
“Do you blame him?”
“No.”
“Your commander?”
Pike took longer.
“Some.”
“Yourself?”
He laughed without humor.
“Mostly.”
I leaned against the railing.
“So yesterday when you were screaming about rank—”
“I wasn’t trying to impress you.”
“You were extremely convincing.”
“I wanted command notified because the preliminary report said driver error.”
My head turned.
“What?”
“Before I even reached your hospital.”
“That fast?”
“Yes.”
“Who told you?”
“The corpsman showed me the transfer note.”
“What did it say?”
“Single-vehicle rollover following driver loss of control.”
“That doesn’t necessarily assign blame.”
“It leaves out eighteen hours of training.”
He looked at me.
“And a reported steering problem.”
That mattered.
“Reported by whom?”
“Foster.”
“When?”
“Two days earlier.”
“Was the vehicle inspected?”
“I don’t know.”
He looked away.
“I was trying to reach my command before somebody made the story permanent.”
That finally made his behavior make sense.
Not excuse it.
Explain it.
“Then why demand someone with rank at the hospital?”
“Because I was scared.”
He said it cleanly.
No performance.
No excuse.
“I thought if I could get somebody senior enough to call somebody senior, I could stop the paperwork.”
“You were trying to command a medical problem.”
“Yes.”
“And nearly ignored the medical problem killing you.”
“Yes.”
I nodded.
“Good talk.”
He laughed, then grabbed his ribs.
“Don’t.”
“Your fault.”
He looked toward me.
“Can I ask one thing?”
“You’ve already exceeded your allowance.”
“What would you have done differently in 2019?”
My answer came immediately.
“Everything.”
“That isn’t an answer.”
“It’s the only one my brain likes.”
“What would you actually change?”
I looked at him.
He was serious.
I thought about weather briefings.
Casualty reports.
Aircraft limitations.
Command pressure.
My own certainty.
“Maybe nothing.”
His eyebrows lifted.
“That’s the part I can’t live with.”
He understood.
“Same.”
We stood there for a while.
Two people haunted by decisions that might have been reasonable.
That afternoon, Pike’s situation became more complicated.
The Navy safety office contacted him.
His training command had already submitted an initial mishap summary.
Driver fatigue was mentioned.
Extended training hours were not.
Neither was the steering complaint.
Pike asked me what he should do.
“I’m your nurse.”
“You used to command people.”
“Used to.”
“So?”
“So call the investigator and tell the truth.”
“What if it destroys my commander?”
“Truth isn’t a weapon unless you shape it into one.”
“That sounds rehearsed.”
“It took six years.”
He nodded.
Then asked for the phone.
I handed it to him.
He made the call himself.
That mattered.
He did not ask me to make his fight mine.
Two days later, another fight arrived.
Risk management completed my chart review.
No scope violation.
No inappropriate intervention.
No failure to follow escalation procedure.
I should have been cleared.
Instead, Dr. Mercer requested formal review of “professional conduct and chain-of-command behavior.”
Beth Lang told me in her office.
“He wants a performance improvement plan.”
“For what?”
“Communication.”
I laughed.
She didn’t.
“You did call him wrong in front of staff.”
“I called for a repeat ultrasound.”
“You also told him he was making this about being wrong.”
“Afterward.”
“I know.”
She rubbed her forehead.
“Claire, I’m on your side clinically.”
“That sentence has a second half.”
“You can’t keep cutting people open verbally and then claiming accuracy makes it sterile.”
That landed.
Because she was right.
I sat back.
“What do you recommend?”
“Agree to communication coaching.”
“You cannot be serious.”
“I am.”
“I saved his patient.”
“You helped recognize his patient was deteriorating.”
“Fine.”
“And now you’re doing it again.”
“What?”
“Turning everything into a battlefield.”
I said nothing.
Beth softened.
“You don’t have to win every conversation to protect the patient.”
I stared at my hands.
That had been easier in the military.
Mission.
Role.
Authority.
Escalation.
Civilian hospitals were messier.
People worked together for years.
Pride mattered even when it shouldn’t.
Relationships affected whether someone listened the next time.
“I’ll do the coaching.”
Beth blinked.
“That easy?”
“No.”
I stood.
“But you’re right.”
The door opened.
Dr. Mercer stood outside.
He had heard enough to look uncomfortable.
“Claire.”
“Malcolm.”
He entered.
Beth stayed.
Good.
Mercer held a document.
“I’m withdrawing the request.”
I frowned.
“Why?”
“Because I read the full timeline again.”
“And?”
“You escalated appropriately.”
“We established that.”
“Yes.”
His jaw tightened.
Then he did something I had not expected.
“I didn’t.”
Silence.
“The first time you requested repeat imaging, I dismissed you because I had already decided his decline was pain and medication.”
I said nothing.
He continued.
“When you pushed again, I heard challenge instead of information.”
Beth leaned back.
Mercer looked at me.
“That was my failure.”
I wanted to make it easy for him.
Say no harm done.
Say we were both tired.
But there had nearly been harm.
So I said:
“Thank you.”
Nothing more.
Then I added:
“I was unnecessarily personal afterward.”
His expression changed.
“You were.”
“I’m sorry.”
“Thank you.”
It wasn’t friendship.
It was better.
It was usable.
Then Mercer looked toward my covered arm.
“For what it’s worth, your old rank doesn’t matter to me.”
“That’s good.”
“You’re still irritating.”
“That’s better.”
For the first time since Pike entered the hospital, I laughed.





