The Injured Admiral Refused Every Doctor—Then the Quiet Nurse Called Him “Ridgeline” and He Whispered, “Sable?”
PART 2
The USS Franklin Pierce incident happened ten years earlier.
Kate had been thirty-two.
Lieutenant.
Navy critical-care nurse.
Temporary expeditionary medical support team.
She was supposed to be aboard for six days.
On day four, a maintenance evolution in an electrical distribution room produced an arc flash and fire.
Automatic suppression limited spread.
But smoke moved.
Sailors evacuating through narrow passageways collided.
One fell down ladder.
Another fractured ankle.
Three inhaled enough smoke to require aggressive respiratory support.
One electrician sustained burns to hands and neck.
Nothing about it made national news.
No enemy.
No dramatic rescue footage.
Just a ship full of people suddenly needing different skills than they expected that afternoon.
Captain Vale, then forty-nine, became one of the officers coordinating casualty movement.
Kate first met him because he carried an injured sailor into casualty receiving while bleeding through his own sleeve.
She said:
“Sit.”
He said:
“I’m fine.”
She said:
“You are dripping on my floor.”
He looked down.
Apparently surprised blood applied to him too.
He sat.
That became first Northstar/Harbor exchange.
During mass-casualty management, informal radio shorthand appeared.
Medical receiving point:
Harbor.
Command liaison:
Northstar.
The names lasted less than one day.
But stress stamped them deeply.
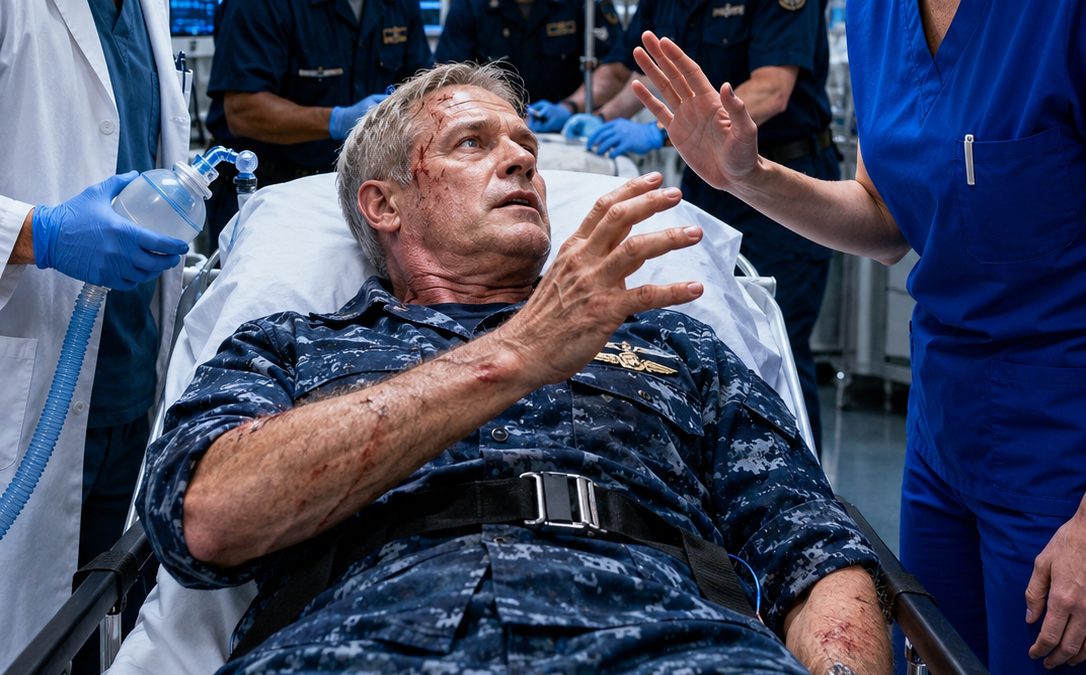
Later, Vale’s oxygen saturation dropped after prolonged smoke exposure.
He became agitated when a tight oxygen mask covered his mouth.
Kate noticed he repeatedly said:
“I can’t hear you.”
Someone answered louder.
Did not help.
Then Kate realized:
He was reading mouths.
Left hearing loss.
Crowded, smoky compartment.
Mask removed visual information.
They adjusted communication.
One person at time.
Face visible when possible.
Right side.
Brief sentences.
Vale settled.
Medical treatment worked better.
No miracle.
Just adaptation.
Years later he remembered.
So did she.
Now in San Diego hospital, the same pattern returned.
Age.
Concussion.
Pain.
Removed hearing aids during field stabilization.
Masked strangers.
Hands.
Noise.
His brain interpreted uncertainty as threat.
Kate’s old call sign did not hypnotize him.
It gave one recognizable anchor.
Then good team behavior did rest.
Next morning Vale woke in monitored room.
His daughter Anna had arrived from Seattle.
Forty.
Attorney.
She thanked Kate.
Kate said:
“You don’t owe me anything.”
“My father says you saved his life twice.”
“No.”
Anna smiled.
“He’s dramatic when medicated.”
“Always was.”
Vale called from bed:
“I can hear you.”
Kate leaned into doorway.
“Apparently only insults.”
He looked better.
Still bruised.
Left arm supported.
Oxygen low-flow.
He said:
“Why are you working nights here?”
Kate answered:
“Because this is where my job is.”
“That’s not what I asked.”
“I know.”
Anna looked between them.
“Do you two always talk like this?”
“Yes.”
“No.”
Simultaneously.
Good.
Vale eventually asked:
“What happened after Franklin Pierce?”
Kate had transferred.
Then flight nursing.
Guam.
Hawaii.
San Diego.
Her father’s diagnosis.
Divorce.
Leaving active duty.
She explained without drama.
Vale listened.
“You were on promotion list.”
“Yes.”
“You walked away?”
“I separated.”
“Different.”
“Fine.”
“Why?”
“My father needed somebody.”
Vale frowned.
“You had siblings.”
“One brother.”
“He had three kids.”
“That doesn’t make you automatically responsible.”
Kate’s jaw tightened.
“Sir.”
He stopped.
Old rank reflex.
Then corrected.
“Kate.”
“You don’t have to answer.”
She nodded.
This mattered.
At thirty-nine, Kate had told herself leaving active duty was pure choice.
Mostly true.
But she had also made decision under:
Father falling repeatedly.
Mother already deceased.
Marriage failing.
Insomnia.
Guilt.
Command offering one more demanding billet.
She did not regret separating.
She did regret believing capable people were supposed to absorb every gap.
Her father died eighteen months later.
By then marriage finished.
Kate rented small apartment.
Took six months off.
Then returned as civilian RN.
No hidden mission.
No federal debrief.
No file marked inactive.
Just a woman rebuilding ordinary work.
Grace later asked in break room:
“You were Nurse Corps?”
“Yes.”
“How long?”
“Ten years.”
“Critical care?”
“Yes.”
“Flight?”
“Some.”
Grace stared.
“And you let me spend three years explaining supply carts to you.”
Kate smiled.
“You were very thorough.”
“Why didn’t you tell us?”
“Tell you what?”
“All of it.”
Kate thought.
“Would it have changed how you treated me?”
Grace opened mouth.
Closed.
That answer worried her.
Because yes.
Probably.
People respected Kate already.
But biography would have changed assumptions.
And that was precisely problem.
Professional respect should not depend on discovering impressive old résumé.
Grace said:
“I’m sorry.”
“For?”
“I think I assumed quiet meant inexperienced.”
Kate nodded.
“You did.”
No reassurance.
Grace accepted.
Then:
“I’ll do better.”
“Good.”
That was enough.
PART 3
The hospital reviewed Vale’s first fifteen minutes of care.
Not because someone had committed misconduct.
Because his agitation exposed a systems problem.
Trauma intake documented:
Hearing impairment?
Unknown.
Assistive device?
Removed during field care.
Communication preference?
Unknown.
Baseline cognition?
Unknown.
All reasonable in emergency.
But there was no quick visual cue during high-acuity handoff showing:
PATIENT HAS SEVERE LEFT-SIDED HEARING LOSS.
Emergency medical team had mentioned hearing aids in narrative handoff.
The detail disappeared among:
Mechanism.
Vitals.
Medications.
Injuries.
Loss of consciousness.
Too much information.
Kate suggested something simple.
For patients with major sensory or communication needs during resuscitation:
One designated handoff field.
HEARING / VISION / COMMUNICATION BASELINE.
Not a new ten-page policy.
One line.
If known.
Examples:
Deaf, uses ASL.
Severe hearing loss right ear.
Needs glasses to lip-read.
Primary language.
Speech device.
Dementia baseline.
No guarantee.
But visible.
The trauma committee adopted trial.
Dr. Ellery supported.
Important.
He was not villain.
He had initially focused on restraint and sedation because Vale was pulling lines and pushing staff.
Reasonable.
Once new information came, he changed.
That was competence too.
Kate told residents during debrief:
“Don’t rewrite event as ‘we should have known.’”
“You didn’t.”
“The question is how information reaches room next time.”
A resident asked:
“Would sedation have been wrong?”
“No.”
“If he remained danger to himself or staff, sedation could be necessary.”
“But reducing avoidable triggers may make less medication possible.”
“Both can be true.”
Good medicine rarely fit social-media moral.
Weeks later Vale returned for follow-up.
Civilian clothes.
Sling gone.
Walking slowly.
He brought Kate a framed photograph.
She hated gifts.
“What is this?”
Franklin Pierce casualty-receiving team.
Twenty people.
Kate in old Navy uniform near edge.
Vale with wrist splint.
“What am I supposed to do with this?”
“Remember you existed before night shift.”
“That seems unnecessary.”
He smiled.
Then serious:
“I owe you apology.”
“For?”
“Franklin Pierce.”
She frowned.
“You thanked team.”
“I thanked team publicly.”
“I never thanked you individually.”
“That’s fine.”
“No.”
“Let old man finish.”
Kate did.
Vale said:
“You were the person who realized I wasn’t fighting oxygen.”
“I was fighting not understanding.”
“That distinction stayed with me.”
Kate looked at photo.
“Honestly?”
“Yes.”
“I barely remember treating your wrist.”
He laughed.
“Excellent.”
Memory was selective.
Vale remembered her as central.
Kate remembered:
Three respiratory patients.
One burn patient.
A corpsman named Ellis dropping an entire tray of IV starts.
The smell of smoke.
A coffee she never drank.
Perspective.
No single story owned event.
Vale said:
“I’m retiring next year.”
“Congratulations.”
“I hate it.”
“Also congratulations.”
He asked if she would speak at Navy medical leadership conference about communication under stress.
Kate declined.
“No.”
“Why?”
“I’m staff nurse.”
“That is exactly why.”
“No.”
He did not pressure.
Good.
Two months later Grace asked same thing.
Kate said:
“You too?”
“Yes.”
“Why?”
“Because our new nurses should hear it.”
Kate thought.
She agreed to twenty minutes internally.
No conference.
The session was titled:
WHEN “COMBATIVE” IS AN OBSERVATION, NOT AN EXPLANATION.
Kate began:
“Combative behavior is real.”
“Safety matters.”
“But label does not tell you cause.”
Pain.
Hypoxia.
Delirium.
Fear.
Substance use.
Brain injury.
Sensory impairment.
Prior trauma.
Medication reaction.
Many possibilities.
“Secure immediate danger first.”
“Then keep asking what changed and what information patient has access to.”
She told Vale case de-identified.
One nurse asked:
“How did you know?”
“I had prior history.”
“So intuition?”
“No.”
“Memory.”
“Different.”
Kate disliked mystical expertise.
Expertise often looked like instinct because people forgot years behind it.
But instinct still needed verification.
Vale recognized call sign.
Then hearing history was confirmed later through records and daughter.
Good.
She added:
“Never assume old knowledge is current.”
That became key.
Ten years earlier Vale had left hearing loss.
Could have changed.
Maybe cochlear device.
Maybe new condition.
Kate used old history as hypothesis.
Not final chart.
This distinction became her teaching style.
Observation.
Hypothesis.
Verify.
Update.





