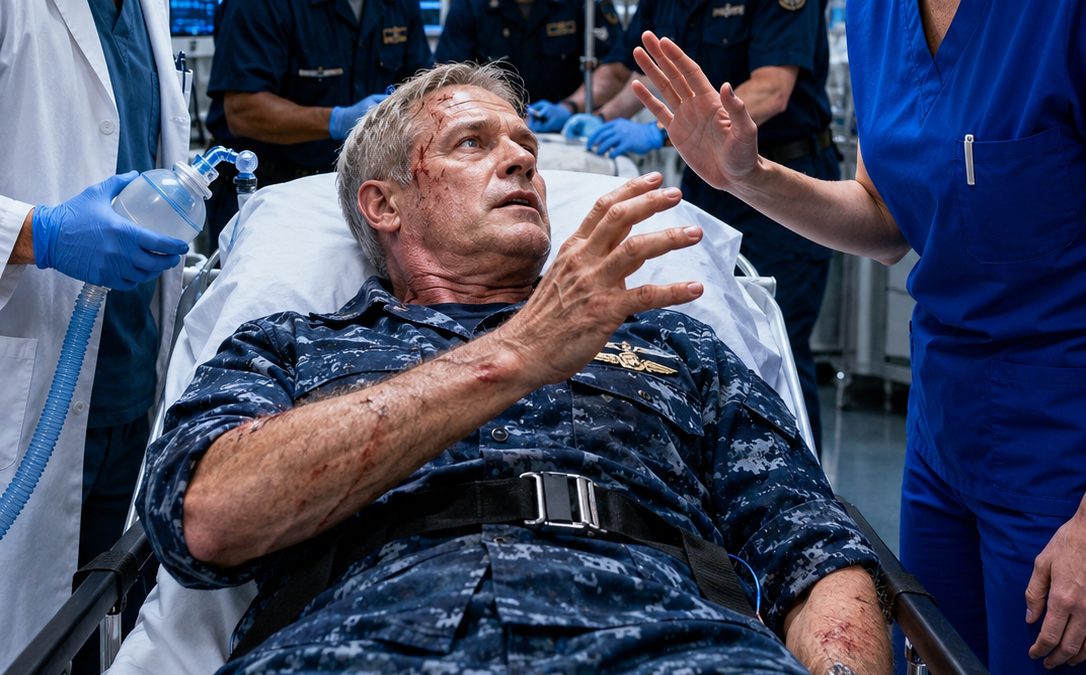
The Injured Admiral Refused Every Doctor—Then the Quiet Nurse Called Him “Ridgeline” and He Whispered, “Sable?”
PART 4
A year later Thomas Vale retired.
No helicopter flyover.
No enormous ceremony.
A modest change-of-command event.
Family.
Officers.
Sailors.
Kate attended only because Anna threatened to drive to hospital and embarrass her.
Vale saw her.
“Harbor.”
Kate pointed.
“Civilian now.”
“You too.”
“Northstar.”
He laughed.
That was perhaps last time they used call signs for years.
Vale moved to Washington.
Volunteered with maritime museum.
Complained about retirement.
Then discovered grandchildren made schedules whether he liked them.
Kate stayed at Naval Medical Center.
At forty-five she accepted clinical educator role half time.
Only half.
She refused management.
She still worked two bedside shifts weekly.
Why?
Because teaching untethered from current practice could become stale.
Her father had been machinist.
He used to say:
“Don’t teach somebody a wrench you haven’t held in ten years.”
Probably not evidence-based educational theory.
Useful anyway.
Kate’s relationship with Grace became friendship.
They ate breakfast after night shifts.
Argued about coffee.
Grace eventually asked:
“Do you miss active duty?”
“Yes.”
“Would you go back?”
“No.”
“How can both be true?”
Kate smiled.
“People keep asking that.”
Missing something did not make departure wrong.
Leaving could cost.
Still be correct.
At forty-seven, Kate tore rotator cuff lifting? Better no workplace injury if avoid nurse unsafe lifting. She developed shoulder degeneration from old injury and needed surgery.
For six weeks she could not work bedside.
Hated help.
Grace drove her home.
Carried groceries.
Kate said:
“I can carry that.”
“No.”
“I have one good arm.”
“You also have discharge instructions.”
Kate glared.
Grace said:
“This must be what your father went through.”
That landed too hard.
Kate stopped.
Her father had hated needing assistance.
She responded by taking over.
Appointments.
Medication boxes.
Finances.
Home modifications.
Sometimes before asking.
She had believed efficiency was kindness.
Maybe sometimes.
Maybe not always.
Recovery forced her to practice:
Can you help me?
Could you put this there?
No, I can do that part.
Specific.
Better than helpless or controlling.
When she returned, she added something to teaching:
Competence includes accepting role changes.
Patient may be admiral.
Nurse may be former officer.
None changes current clinical roles.
Person with most past experience is not automatically current authority.
That was where original dramatic stories got things wrong.
Rank could not substitute for credentialing.
Call sign could not authorize procedure.
Past trauma skills could inform.
But hospital team still needed:
Scope.
Orders.
Protocols.
Communication.
She told trainees:
“If I know something important, I speak.”
“If someone else owns decision, they decide.”
“If I think decision unsafe, I escalate through chain.”
“That is not weakness.”
“That is how complex systems avoid depending on one genius in room.”
Good.
At fifty Kate finally accepted invitation to larger military medicine conference.
Her title:
THE INFORMATION THAT FALLS OUT OF HANDOFFS.
Not:
Secret Nurse Saves Admiral.
Vale attended anonymously in back row.
During Q&A a physician asked:
“What was most important intervention?”
Kate answered:
“Reducing communication mismatch.”
“Not the call sign?”
“The call sign got his attention.”
“It wasn’t treatment.”
Vale raised hand from back.
“You undersell yourself.”
Kate squinted.
“You are not part of panel.”
Audience laughed.
He introduced himself.
Then said:
“She’s right.”
“That word didn’t fix injuries.”
“It gave me one familiar point.”
“After that, the medical team could do their jobs.”
Better.
No hero monopoly.
PART 5
Fifteen years after that night, Kate Sullivan was fifty-seven.
Rear Admiral Thomas Vale was seventy-eight.
Retired.
Hearing worse.
Grandchildren louder.
Still alive.
Still difficult.
He came to San Diego for cardiac procedure at civilian hospital.
Nothing dramatic.
Planned valve replacement.
Before admission Anna called Kate.
“Dad says he wants Harbor on standby.”
Kate laughed.
“Absolutely not.”
“He’s joking.”
“He is not.”
Vale yelled in background:
“I CAN HEAR YOU.”
Kate replied:
“Then stop making daughter translate.”
Good.
She visited after procedure.
Vale looked small in hospital bed.
Age did that.
No uniform.
No command presence.
Just person recovering.
He said:
“You know what I remember most from that night?”
“What?”
“Not Northstar.”
Kate waited.
“You told everyone to approach from my right.”
“That’s it?”
“Yes.”
“I had no idea why room suddenly made sense.”
Interesting.
Patients often remembered different intervention than clinicians.
Kate had remembered call sign.
Vale remembered people becoming understandable.
He said:
“I spent career thinking control meant having complete picture.”
“Then one concussion reminded me how quickly picture disappears.”
Kate smiled.
“You were concussed.”
“You still are occasionally.”
Vale ignored.
He asked:
“Do your nurses know who you used to be now?”
“Some.”
“Does it matter?”
“Less.”
“Good.”
After Vale returned Washington, Kate prepared retirement.
Not complete.
One day weekly simulation teaching.
No bedside.
At farewell, younger nurse named Priya gave speech.
“She taught us three annoying questions.”
Everyone knew:
What did you observe?
What are you assuming?
What would change your mind?
Kate had stolen framework from decades of medicine and maintenance-minded father.
It became hers by repetition.
Priya continued:
“She also taught us never to confuse being quiet with having nothing to say.”
Kate looked down.
That one mattered.
Early career she had been loud enough.
Command briefs.
Codes.
Flights.
Then life hit.
She became quieter.
Coworkers assumed:
Reserved.
Junior.
Uncertain.
Sometimes they were wrong.
But Kate also learned another truth.
Quiet people could not expect systems to discover what they knew automatically.
She had responsibility too.
If relevant expertise existed, speak.
Not wait for dramatic moment.
After Vale incident she updated internal skills profile.
Critical care background.
Flight nursing history.
Military trauma experience.
Educator credentials.
Not vanity.
Resource visibility.
Hospital could use people better when capabilities known.
She encouraged others:
Paramedic before nursing?
Record it.
Interpreter certification?
Record.
Wound-care expertise?
Record.
Not so management can exploit you.
So unusual capability does not exist only in hallway rumor.
At sixty-two Kate fully retired.
She moved north to small town near her sister.
Garden.
Bad at tomatoes.
Good at roses.
Vale died at eighty-three after short illness.
Anna called.
Peaceful.
Family there.
No unfinished rescue.
Kate attended memorial online.
His grandson told story about grandfather losing hearing aids in a lake.
Far better than military biography.
Afterward Anna mailed small envelope.
Inside:
Old Franklin Pierce photograph.
Vale had written on back years earlier:
HARBOR KNEW I COULDN’T HEAR BEFORE I DID.
Kate laughed.
Technically he knew.
Just not in that moment.
She kept photo.
Years later one of her former students sent viral video.
Title:
INJURED ADMIRAL REFUSES EVERY DOCTOR UNTIL SECRET MILITARY NURSE USES CLASSIFIED CALL SIGN.
Kate watched twelve seconds.
Turned off.
Sent:
ABSOLUTELY NOT.
Priya replied:
BUT VERY COOL.
Kate:
HE HAD A CONCUSSION AND NO HEARING AIDS.
Priya:
LESS COOL.
Kate:
MORE USEFUL.
Exactly.
The actual lesson could repeat.
A confused older patient fighting a mask.
A child who cannot understand instructions.
A deaf patient without interpreter.
A person with dementia waking somewhere unfamiliar.
A trauma survivor reacting to restraint.
A frightened patient being labeled difficult when information channel itself had broken.
None required secret identity.
They required curiosity.
And humility.
Kate eventually wrote one page for nursing newsletter:
Before you decide a patient is refusing care, ask whether they understand what is being offered.
Can they hear you?
See you?
Understand language?
Know where they are?
Recognize who is touching them?
Are they in pain?
Hypoxic?
Delirious?
Afraid?
Then:
Maintain safety.
Explain.
Verify.
Escalate appropriately.
No heroics.
That page became more useful than any legend.
At seventy-one Kate visited San Diego once more.
Hospital remodeled.
Trauma bay different.
Grace long retired.
Aaron Ellery teaching at university.
New nurses who had never heard Vale’s name.
Good.
She sat near harbor with coffee.
Thought about that night.
A man on gurney.
Hands pushing.
Too many voices.
One old word.
Northstar.
For years people told story as though word exposed who Kate “really was.”
It did not.
Kate had always been Kate.
Navy officer.
Daughter.
Divorced woman.
Caregiver.
Civilian nurse.
Educator.
Retiree.
None more true than another.
The revelation was smaller.
A room had assumed the quiet nurse standing near cabinet had nothing relevant to add.
She did.
Then she spoke.
The team listened.
And because they listened, they learned enough about patient to make good medicine easier.
That was all.
It was also enough.
Kate finished coffee.
A Navy helicopter crossed distant sky.
She looked up.
Watched until gone.
No ache requiring repair.
No call sign needed.
Just memory.
Then she stood.
And went home.
THE END
This story is entirely fictional. All characters and events are created for entertainment purposes only.





